Home » Treatment » Liothyronine Sodium 20 microgram tablets
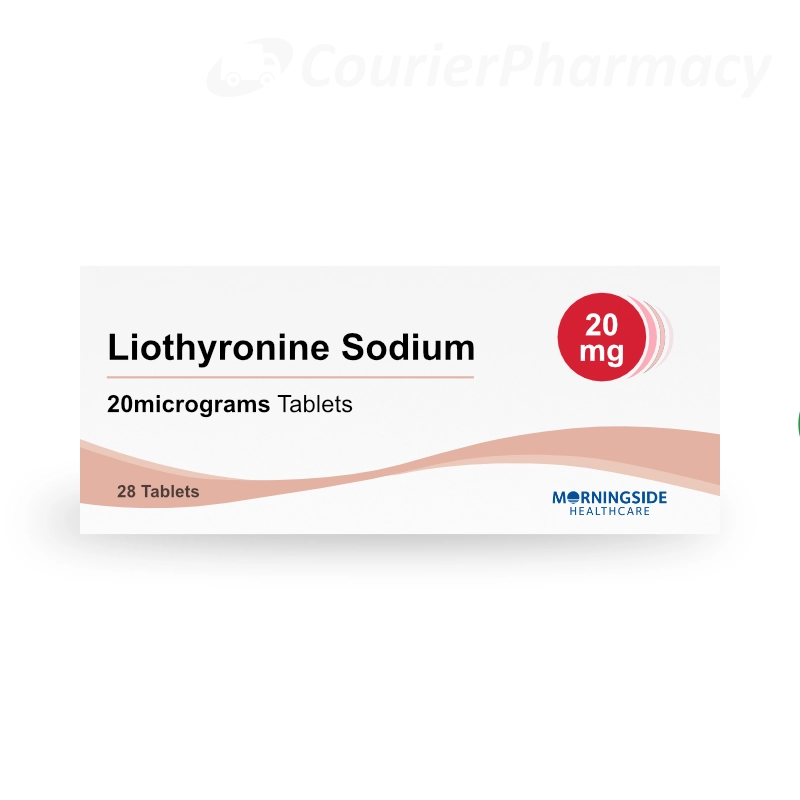
Liothyronine Sodium 20 microgram tablets
from£49.99
Specialist second-line T3 thyroid hormone for hypothyroidism, usually used in combination with levothyroxine
Contains 20 micrograms of liothyronine sodium (T3) per tablet, the biologically active thyroid hormone
Requires 2-3 daily doses due to short half-life. Rapid onset and offset compared with levothyroxine
NICE does NOT recommend routine use. Only appropriate after specialist endocrinologist assessment
28-tablet pack. Prescription-only after specialist review. Available from Courier Pharmacy for established patients through our online prescriber service
Liothyronine 20 microgram tablets are a UK-licensed prescription-only thyroid hormone medicine. Each tablet contains 20 micrograms of liothyronine sodium, the synthetic form of T3 (triiodothyronine).
Notably, T3 is the biologically active thyroid hormone. Your body normally makes only small amounts of T3 directly. Most of your T3 is made by converting T4 (thyroxine) in your tissues using enzymes called deiodinases. So liothyronine bypasses this conversion step by supplying T3 directly.
Why 20 microgram is a common strength
Liothyronine 20mcg is one of three UK-licensed strengths (alongside 5mcg and 10mcg tablets). Because typical adult doses fall in the 20-60 microgram daily range, the 20mcg strength is central to most treatment regimens.
The 20mcg strength also enables convenient dose combinations. For example, a patient on 40mcg daily takes two 20mcg tablets in divided doses. A patient on 30mcg daily takes 20mcg plus 10mcg. So the 20mcg strength supports a wide range of individual dosing needs.
Second-line specialist status
Liothyronine sits firmly in second-line thyroid treatment. The UK-licensed Summary of Product Characteristics states: ‘liothyronine sodium may be preferred for treating severe and acute hypothyroid states because of its rapid and more potent effect, but thyroxine sodium is normally the drug of choice for routine replacement therapy’.
NICE Guideline NG145 (2019) further recommends against routine use in primary hypothyroidism. However, BTA guidance supports careful supervised trials in specific patients who remain symptomatic on adequate levothyroxine alone.
So the typical patient prescribed liothyronine has already tried levothyroxine, achieved normal TSH but continued to feel unwell, and been assessed by an endocrinologist for a trial of combination therapy.
The 28-tablet pack duration
The 28-tablet pack lasts different lengths depending on your daily dose and frequency:
1 tablet daily = 28 days (unusual for T3, but possible in combination with T4)
1 tablet twice daily = 14 days
1 tablet three times daily = around 9 days
Half a tablet twice daily = 28 days (if 20mcg split into 10mcg doses)
So one pack may last from around 9 days to a full month depending on your regimen. Also, most patients on liothyronine also take levothyroxine as part of combination therapy, so you may need both prescriptions.
Historical UK pricing context
Liothyronine has an unusual pricing history in the UK. Between 2007 and 2016, the NHS price rose by around 6,000%, reaching over £250 per pack of 28 tablets. Because of this, the Competition and Markets Authority (CMA) investigated and fined Concordia (then the main supplier) £84 million in 2019.
Prices have since come down considerably following generic competition. Notably, the current NHS tariff price is around £50 per pack of 28, which is much better but still much more expensive than levothyroxine.
Key features and details
Active ingredient: liothyronine sodium 20 micrograms per tablet
Class: synthetic thyroid hormone (T3, active form)
Form: white, uncoated, biconvex tablet, debossed with ‘T3’
Pack size: 28 tablets
Legal status: Prescription-Only Medicine (POM)
For: adults (specialist prescribing). Also licensed for children under paediatric endocrinology supervision
Standard dose range: 20-60mcg daily in 2-3 divided doses (varies with clinical situation)
Timing: multiple daily doses due to short half-life. Some prescribers advise empty stomach, though evidence is less clear than for levothyroxine
Storage: below 25°C in original packaging, away from light and moisture
Key features: specialist second-line thyroid treatment; rapid onset; fluctuating blood levels; requires specialist-guided monitoring; usually used in combination with levothyroxine
Additional information
Quantity
1 x 28, 2 x 28, 3 x 28
MOJO WISDOM
Take control of your health by understanding your condition and what this medication is doing for you.
READ:
More information about this treatment.
UK-based doctors and pharmacists
Discreet and Confidential
UK-based doctors and pharmacists
Free, Expert Advice
No video link provided.
No video link provided.
UK-based doctors and pharmacists
Free, expert advice
Discrete and confidential
Fast delivery
Giving you trusted clinical advice for over 40 conditions
A UK regulated pharmacy providing safe, effective treatments online since 2014
A prescription-only synthetic T3 thyroid hormone (triiodothyronine), used as second-line specialist treatment for hypothyroidism.
Biologically active form of thyroid hormone. Rapid onset (hours) but short-lasting (half-life ~1 day).
Usually taken in 2-3 divided doses through the day, most often in combination with levothyroxine (T4).
NICE does NOT recommend routine use. Only appropriate after specialist endocrinologist assessment and trial.
Prescription-only after specialist assessment. Requires ongoing monitoring. Available from Courier Pharmacy for established patients through our online prescriber service.
Where liothyronine fits in thyroid treatment
Thyroid hormone replacement in hypothyroidism uses a stepped approach. Because levothyroxine (T4) works well for most patients and has a much longer safety track record, it’s the first-line treatment for essentially everyone with newly diagnosed hypothyroidism.
Liothyronine (T3) enters the picture only after: adequate T4 dosing has achieved normal TSH; the patient continues to have significant symptoms; other causes of persistent symptoms have been ruled out; and specialist endocrinology assessment has considered T4+T3 combination trial appropriate. So this represents a small minority of hypothyroid patients.
Liothyronine vs Levothyroxine
Levothyroxine (T4) is the first-line treatment for essentially all hypothyroidism. It’s much cheaper, needs just once daily dosing (versus 2-3 times daily for T3), has a longer safety record, and works well for most patients.
So most patients should try levothyroxine monotherapy first, with adequate dose titration and time to fully assess response, before considering liothyronine.
Liothyronine + Levothyroxine combination therapy
Combination therapy adds low-dose T3 to existing levothyroxine. Because the aim is to more closely replicate normal thyroid physiology, T4 doses are usually reduced when T3 is added.
However, evidence for benefit of combination therapy over levothyroxine alone is mixed. Some patients report significant symptom improvement, while randomised trials have generally not shown clear group-level benefit. So specialist judgment on individual response is key.
Liothyronine vs Natural Desiccated Thyroid (NDT)
Natural desiccated thyroid (Armour Thyroid, Nature-Throid, Erfa Thyroid) is a preparation made from dried pig thyroid. It contains both T4 and T3 in a fixed ratio. Because it’s unlicensed in the UK and quality control varies, NICE and UK guidance don’t support routine NDT prescribing.
So licensed liothyronine (with or without levothyroxine) is generally preferred over NDT in the UK when T3 supplementation is being considered.
Liothyronine 20mcg vs 5mcg or 10mcg
5mcg and 10mcg tablets are available for finer dose titration. However, they’re usually more expensive per microgram than 20mcg tablets. So many patients use 20mcg tablets split or dissolved to achieve smaller doses if cost is a factor.
Liothyronine vs compounded T3
Compounded or specials T3 preparations exist but aren’t recommended when licensed products are available. Because licensed products have consistent quality and dose accuracy, they’re preferred where they meet clinical needs.
Alongside supportive lifestyle measures
Thyroid treatment works best alongside good general health measures: regular sleep, balanced diet (with adequate iodine, selenium, iron, and other trace nutrients), regular exercise, and stress management. Also, treating coexisting conditions like iron deficiency, vitamin D deficiency, and B12 deficiency can improve energy and wellbeing alongside thyroid replacement.
Why choose Courier Pharmacy for your Liothyronine
Specialist endocrinology expertise
Our prescribers have special interests in endocrinology and have MSc in Endocrinology, which is particularly relevant for thyroid conditions and combination T4/T3 therapy. So thyroid replacement complexity, including liothyronine dosing decisions, sits within their area of clinical expertise.
Registered, independent, and prescriber-led
Courier Pharmacy is a UK-registered independent pharmacy with independent prescribers on-site. The General Pharmaceutical Council regulates us. So when you request liothyronine through our service, a qualified prescriber assesses your situation before prescribing.
Dr Ada Jex-Cori, our brand pharmacist
Our brand pharmacist is Dr Ada Jex-Cori. She represents the spirit of what we do. Named for Ada Lovelace, Sophia Jex-Blake, and Gerty Cori, she stands for evidence-led, unafraid-of-questions medicine. Her message is straightforward. You’re not broken. The system is. We’re here to change that.
Care that keeps showing up
Liothyronine treatment is usually long-term but should be reviewed periodically. So we’re here for the follow-up: coordinating repeat prescriptions between specialist reviews, discussing monitoring blood tests, helping troubleshoot symptom fluctuations, and stepping back to endocrinologist referral when situations change.
Buy Liothyronine 20 microgram Tablets from Courier Pharmacy
Liothyronine 20mcg tablets are a Prescription-Only Medicine. You can request supply through our online prescriber service at courierpharmacy.co.uk for patients already established on liothyronine under specialist supervision.
Complete our online consultation, providing details of your hypothyroidism diagnosis, current liothyronine dose and regimen, most recent fT3/fT4/TSH results, name of specialist endocrinologist involved, other medicines you take, and any concerns
Our independent prescriber reviews your case. If liothyronine is appropriate to supply, a prescription is issued
The 28-tablet pack is dispatched promptly, usually next working day
Take exactly as directed. Keep up with regular blood tests and endocrinologist reviews. Contact us if concerns arise
If liothyronine isn’t right for your current situation, we’ll explain why. Options include stable-dose levothyroxine monotherapy (first-line for essentially all hypothyroidism), levothyroxine at different strengths (25mcg, 50mcg, 75mcg, 100mcg, 150mcg, 200mcg tablets, or oral solution), different liothyronine strengths (5mcg or 10mcg tablets for finer dosing), specific brand requests (Roma, Morningside, Advanz, Thybon Hennings), referral to a specialist endocrinologist for combination therapy assessment (essential for new initiations) or a private telephone consultation with one of our prescribers if NHS access is limited, or advice on managing coexisting conditions that affect thyroid function (iron deficiency, vitamin D deficiency, B12 deficiency).
Above all, we won’t supply liothyronine to patients not established under specialist care, and we’ll flag when your monitoring or endocrinologist review is overdue.
Active ingredient in Liothyronine 20 microgram Tablets
Liothyronine sodium 20 micrograms per tablet
Liothyronine sodium is the synthetic form of T3 (triiodothyronine), the biologically active thyroid hormone. Because your body's cells respond to T3 by binding to thyroid hormone receptors in cell nuclei, T3 directly triggers all the metabolic effects of thyroid hormone.
T3 contains three iodine atoms (hence the name triiodothyronine), one fewer than T4 (thyroxine). Also, T3 is 3-4 times more potent than T4 on a microgram-for-microgram basis, which is why doses are much smaller (20mcg T3 versus 100mcg T4 for roughly comparable effect).
How T3 differs from T4
Your thyroid gland normally produces both T4 (thyroxine, most of the output) and small amounts of T3 (triiodothyronine, directly active). Because most T3 in your body actually comes from conversion of T4 in tissues (using deiodinase enzymes), T4 acts largely as a prohormone and T3 as the active form.
So the main practical differences between the two hormones are:
Half-life: T4 about 7 days, T3 about 1 day
Onset of action: T4 slow (days-weeks), T3 rapid (hours)
Dosing frequency: T4 once daily, T3 usually 2-3 times daily
Blood level stability: T4 stable, T3 fluctuating through the day
Potency: T3 is 3-4 times more potent by weight
Why T3 supplementation might help some patients
A small proportion of patients on adequate levothyroxine (T4) alone continue to feel unwell despite normal TSH results. So possible explanations include:
However, the evidence for these mechanisms remains debated, and clinical trials of combination therapy versus T4 alone have produced mixed results.
Excipients in Liothyronine 20 microgram Tablets
Standard tablet excipients
Liothyronine tablet excipients vary by manufacturer. Common excipients include: microcrystalline cellulose, magnesium stearate, calcium hydrogen phosphate, sodium starch glycolate, and pregelatinised maize starch. Some brands may contain lactose or other specific excipients.
Because formulation varies by manufacturer, check the pack leaflet for the exact composition of your brand. Notably, some patients may notice differences between brands, and if you have specific dietary requirements, we can confirm the composition of what's being supplied.
Suitability for special diets
Most liothyronine tablet formulations are suitable for vegetarians (check specific brand). Some brands are gluten-free and lactose-free. So if you have specific dietary requirements, ask us to check the composition of the current supply.
What is Liothyronine 20mcg for?
Combination therapy with levothyroxine (main real-world use)
The most common UK use of liothyronine is as an add-on to levothyroxine for patients with persistent hypothyroid symptoms despite normal TSH on T4 alone. Because this is usually a specialist decision after other causes have been excluded, endocrinology involvement is expected.
Severe or acute hypothyroidism (licensed indication)
The UK SmPC licenses liothyronine for severe and acute hypothyroid states, where its rapid onset is helpful. Because these are hospital or specialist situations, this isn't a typical online supply scenario.
Myxoedema coma
Myxoedema coma is a life-threatening severe hypothyroidism emergency, usually managed with intravenous liothyronine in hospital. So oral tablets aren't the treatment for this situation.
Adjunct to carbimazole in hyperthyroidism treatment
When carbimazole is used to treat hyperthyroidism (overactive thyroid), it can sometimes over-suppress thyroid function. So liothyronine may be added to prevent hypothyroidism during carbimazole treatment (called 'block and replace' therapy).
Post-thyroidectomy or thyroid cancer situations
In specific thyroid cancer contexts, particularly before radioactive iodine scanning or treatment, liothyronine may be used because its short half-life allows quicker withdrawal than levothyroxine. So this is a specialist oncology or endocrinology decision.
DIO2 gene polymorphism (emerging area)
Patients with certain DIO2 gene polymorphisms may have reduced T4-to-T3 conversion. Because this may make them more likely to benefit from T3 supplementation, this is being researched. However, routine DIO2 testing isn't currently standard NHS practice.
What liothyronine isn't for
Not first-line for hypothyroidism. Use levothyroxine (T4) first.
Not for weight loss. Because using thyroid hormone for weight loss in people with normal thyroid function is dangerous and doesn't work sustainably, this use is inappropriate.
Not for general fatigue without confirmed hypothyroidism and specialist assessment.
Not for self-initiated treatment. Specialist endocrinologist involvement is expected.
Not for people with untreated adrenal insufficiency. So the adrenal problem must be treated first with corticosteroids.
Not for people with untreated hyperthyroidism.
Not for people with cardiac disease without very careful specialist supervision.
How does Liothyronine work?
Direct action as active thyroid hormone
T3 binds directly to thyroid hormone receptors inside your cells' nuclei. Because these receptors regulate gene expression across many tissues, T3 triggers all the metabolic effects of thyroid hormone: energy production, protein synthesis, cardiac function, temperature regulation, and countless other processes.
Rapid onset
Because you're taking the active hormone directly rather than a prohormone that needs conversion, effects appear within hours rather than weeks. So symptomatic improvements can be noticed relatively quickly, but over-replacement can develop equally quickly.
Short half-life
T3 has a half-life of around 1 day (compared with 7 days for T4). Because of this, blood levels fluctuate significantly through the day, particularly around dose times. So multiple daily doses smooth out these peaks and troughs.
Elimination
Liothyronine is metabolised in the liver and other tissues, with metabolites excreted through bile and urine. Because liver enzyme activity affects metabolism, some drugs that induce liver enzymes (carbamazepine, phenytoin, rifampicin) can increase liothyronine breakdown.
Feedback on TSH
Like all thyroid hormones, T3 suppresses TSH production by the pituitary. However, T3 has a stronger suppressive effect than T4. So TSH is often more suppressed on T3 (or T3+T4 combination) than on T4 alone, which makes TSH less useful as a dose guide.
So free T3 (fT3) and free T4 (fT4) blood tests, along with clinical symptoms, become the main dose guides on liothyronine therapy.
Treatment dosage for Liothyronine 20 microgram
At a glance
For: adults with hypothyroidism requiring specialist second-line treatment
Starting dose (adult): 10-20mcg once or twice daily, sometimes up to every 8 hours
Maintenance range: 20-60mcg daily in 2-3 divided doses (individualised)
Elderly/cardiac: much lower start (2.5-5mcg), very slow titration
Timing: doses spread through the day due to short half-life
Duration: usually long-term once established, but trial period reviewed at 3-6 months
Monitoring: fT3, fT4, and clinical symptoms (TSH interpretation is complicated)
Standard adult dosing (per UK SmPC)
The UK Summary of Product Characteristics recommends a starting dose of 10 or 20 micrograms every 8 hours (three times daily), increasing after one week if necessary, up to the usual daily dose of 60 micrograms in two or three divided doses.
However, real-world dosing varies considerably. Many patients on combination therapy (T3 plus levothyroxine) take much lower T3 doses, such as 5-20mcg daily. Also, some patients split a 20mcg tablet into smaller doses using an oral syringe with dissolved tablet.
Combination therapy with levothyroxine
Most UK patients prescribed liothyronine take it alongside levothyroxine as combination therapy, not as T3 monotherapy. Because combination therapy aims to replicate more normal thyroid physiology, doses are lower than for T3 alone.
When adding T3 to existing levothyroxine, the T4 dose is usually reduced. So a typical adjustment might be: reduce levothyroxine by 25-50mcg daily and add 5-20mcg liothyronine daily in divided doses. Your endocrinologist will make specific recommendations for your case.
Splitting doses through the day
T3 has a short half-life (around 1 day, versus 7 days for T4). Because of this, blood levels fluctuate significantly through the day. So splitting doses helps keep levels reasonably steady.
Practical daily schedules include:
Twice daily: morning and evening (roughly 12 hours apart)
Three times daily: morning, midday, and evening (roughly 8 hours apart)
Combination approach: morning dose paired with levothyroxine, then a second smaller T3 dose in the afternoon
Splitting the 20mcg tablet
Some patients need doses smaller than 20mcg. The UK SmPC allows dissolving the tablet in 20mL of water and drawing up the required amount with an oral syringe. So for a 10mcg dose, dissolve one 20mcg tablet in 20mL water, then take 10mL of the solution.
Alternatively, 5mcg and 10mcg tablets are available separately, though these are usually more expensive than 20mcg tablets. However, ask us about which strength best fits your dose.
Starting doses in elderly and cardiac patients
Older adults and patients with cardiovascular disease need much lower starting doses, often 2.5-5mcg once daily. Because liothyronine can precipitate angina or arrhythmias rapidly, slow titration protects the heart.
Also, TSH targets may need to allow higher values (not fully suppressed) in these groups to avoid over-replacement risks.
Trial period assessment
BTA guidance recommends assessing response to liothyronine after at least 3 months of stable dosing. Because it takes time to fully evaluate benefit and adjust doses, quick judgments miss the point.
However, if there's no clear benefit at 3-6 months of appropriate trial, specialist review to consider stopping and reverting to levothyroxine monotherapy is appropriate.
Pregnancy
Levothyroxine is usually the preferred thyroid hormone in pregnancy because of longer safety data. So if you become pregnant while on liothyronine, contact your endocrinologist urgently. Also, TSH targets tighten during pregnancy, and combination therapy needs careful reassessment.
Breastfeeding
Small amounts of liothyronine pass into breast milk. Specialist input is recommended if breastfeeding on liothyronine, because doses need careful management to avoid affecting the infant.
If you miss a dose
If you miss a dose of liothyronine, take it as soon as you remember. However, if it's close to the next scheduled dose, skip the missed one and continue with your normal schedule. Don't double up.
Because T3 has a short half-life, missed doses cause more noticeable effects than with levothyroxine. However, occasional missed doses still don't usually cause immediate problems if the overall regimen is stable.
How to take Liothyronine 20mcg tablets
Standard use
Take as directed by your endocrinologist or prescriber, usually in divided doses through the day. Swallow tablets whole with water.
Empty stomach timing
Some prescribers advise taking liothyronine on an empty stomach, similar to levothyroxine. However, evidence for empty-stomach dosing is less clear for T3 than for T4. So follow your prescriber's specific advice.
Practical approaches include:
First dose on waking, with water, at least 30 minutes before breakfast
Second dose in early afternoon, at least 2 hours after a meal
Third dose in early evening if using three times daily, at least 2 hours after a meal
Avoid at same meal as iron, calcium, or antacids
Like levothyroxine, liothyronine absorption is reduced by iron, calcium, and antacids. So space by at least 4 hours from any iron supplements, calcium supplements, or antacids like Rennie or Gaviscon.
Space by 2 hours from PPIs
Proton pump inhibitors like omeprazole and lansoprazole reduce stomach acid, which can reduce thyroid hormone absorption. So separate doses by at least 2 hours where practical.
Consistency matters
Take at the same times each day. Because T3 blood levels rise and fall through the day, consistent timing helps keep symptoms stable and makes dose adjustments more predictable.
Splitting the tablet
If your dose is less than 20mcg, you can dissolve the tablet in water and use an oral syringe to measure the exact amount needed. Alternatively, ask your prescriber about lower-strength tablets (5mcg or 10mcg) if these fit your dose better.
Storage
Store the pack below 25°C in the original packaging, away from direct sunlight and moisture. Keep out of reach of children.
Regular monitoring is essential
Because liothyronine dosing is more complex than levothyroxine, regular blood tests (fT3, fT4, TSH) and clinical review are essential. So keep up with the monitoring schedule your endocrinologist recommends, usually every 3-6 months during titration and at least annually when stable.
Warnings and precautions for Liothyronine
Specialist prescribing only
Above all, liothyronine should only be initiated by an endocrinologist or thyroid specialist. Because dosing is complex, monitoring differs from levothyroxine, and risks are higher, specialist supervision matters at least for initiation and periodically thereafter.
Adrenal insufficiency must be treated first
If you have adrenal insufficiency (Addison's disease or hypopituitarism affecting cortisol production), your adrenal problem must be treated with corticosteroids BEFORE starting or increasing liothyronine. Because thyroid hormone speeds up cortisol metabolism, this can precipitate an adrenal crisis in undiagnosed or untreated adrenal insufficiency.
Cardiovascular disease
Patients with angina, previous heart attack, heart failure, or arrhythmias face higher risks with liothyronine than with levothyroxine. Because the rapid onset can precipitate cardiac symptoms, initial doses in these patients should be very low (2.5-5mcg) with slow titration and cardiac monitoring.
So many endocrinologists avoid liothyronine in significant cardiac disease, preferring levothyroxine monotherapy where the safety profile is more established.
Atrial fibrillation risk
Liothyronine (particularly at higher doses or with TSH suppressed below normal) increases atrial fibrillation risk, especially in older adults. So report any palpitations or irregular heartbeat promptly, and periodic ECGs may be recommended.
Osteoporosis and bone density
Long-term thyroid hormone over-replacement (particularly with T3) accelerates bone density loss, increasing osteoporosis and fracture risk. So DEXA scans periodically may be recommended, particularly in postmenopausal women.
Elderly patients
Older adults are more sensitive to thyroid hormone effects and more prone to cardiac and bone complications. So starting doses should be very low (2.5-5mcg), adjustments should be slow, and monitoring should be more frequent.
Pregnancy
Levothyroxine is preferred over liothyronine in pregnancy because of longer safety data and more predictable dosing. So if you become pregnant while on liothyronine, contact your endocrinologist urgently for review.
Breastfeeding
Small amounts of liothyronine pass into breast milk. So specialist input is recommended, particularly at higher T3 doses.
Diabetes
Starting or adjusting liothyronine can affect blood glucose control in diabetes. Because thyroid hormone increases glucose absorption and insulin needs, more frequent blood glucose monitoring is helpful during dose changes.
Long-standing severe hypothyroidism
Patients with very high TSH from long-standing severe hypothyroidism need cautious dose introduction. Because their metabolism has adapted to the low-hormone state, rapid reintroduction can cause cardiac events. So slow titration from very low starting doses is essential.
Signs of over-replacement (more common with T3 than T4)
Report to us or your endocrinologist promptly if you notice: palpitations, fast heart rate, tremor, unusual sweating, heat intolerance, weight loss, anxiety, insomnia, or diarrhoea. So these suggest your dose is too high, and adjustment is needed.
Signs of under-replacement
Report if you notice worsening tiredness, weight gain, cold intolerance, constipation, brain fog, hair thinning, muscle aches, or low mood. So these suggest your dose may be too low, though other causes should be considered too.
Alcohol
Moderate alcohol doesn't interact directly with liothyronine. So normal social drinking is fine.
Driving and machinery
Liothyronine doesn't affect driving or machinery use at appropriate doses. However, unrecognised over-replacement can cause tremor and anxiety that affects concentration.
Side effects of Liothyronine
Side effects mostly relate to over-replacement
At appropriate doses, liothyronine has few side effects because it's replacing a natural hormone. However, over-replacement (which is easier to develop with T3 than T4) causes symptoms of hyperthyroidism.
Symptoms of over-replacement
These include:
Palpitations, fast heart rate
Tremor (particularly in hands)
Anxiety, restlessness, irritability
Difficulty sleeping
Sweating, feeling hot, heat intolerance
Unexplained weight loss
Diarrhoea
Menstrual irregularities in women
Muscle cramps or weakness
Chest pain (particularly in older patients or those with heart disease)
New atrial fibrillation or other arrhythmia
So if you notice these, contact us or your endocrinologist promptly.
Symptoms of under-replacement
These are essentially symptoms of hypothyroidism returning:
Increasing tiredness
Weight gain
Feeling cold, cold intolerance
Constipation
Dry skin, hair thinning
Brain fog, poor concentration
Low mood, depression
So report these too, because they may mean your dose needs adjusting.
Cardiac side effects
Cardiac side effects are more likely with T3 than T4. Watch for chest pain, palpitations, breathlessness, and irregular heartbeat. So report any cardiac symptoms promptly, particularly if you have any cardiac history.
Osteoporosis and fracture risk (particularly in postmenopausal women)
Loss of muscle mass
Cardiovascular events in vulnerable patients
So regular monitoring aims to keep doses appropriate and avoid over-replacement.
Rare allergic reactions
True allergic reactions to liothyronine are extremely rare. However, reactions to tablet excipients can occur. So switching to a different brand often resolves excipient-related sensitivities.
Serious side effects requiring urgent help
Above all, seek urgent medical help for signs of severe allergic reaction (facial or throat swelling, breathing difficulty), chest pain, severe palpitations or new irregular heartbeat, or signs of adrenal crisis (severe weakness, dizziness, low blood pressure, salt cravings). Call 999 if severe.
If you experience side effects, report them via the MHRA Yellow Card scheme at https://yellowcard.mhra.gov.uk/ or search for MHRA Yellow Card in your app store. Reporting helps improve medicine safety for everyone.
Drug interactions with Liothyronine
Iron supplements
Iron reduces liothyronine absorption. So space by at least 4 hours from any iron-containing product (ferrous sulphate, ferrous fumarate, Feroglobin, or multivitamins with iron).
Calcium supplements
Calcium reduces liothyronine absorption. So space by at least 4 hours from calcium supplements or calcium-containing antacids like Rennie, Tums, or Calcichew.
Aluminium and magnesium antacids
Antacids containing aluminium or magnesium (Gaviscon, Maalox) reduce liothyronine absorption. So space by at least 4 hours.
PPIs (proton pump inhibitors)
PPIs like omeprazole, lansoprazole, and esomeprazole reduce stomach acid. Because thyroid hormone absorption partly depends on stomach acid, PPIs can reduce effectiveness. So separating doses by 2+ hours can help.
Warfarin
Liothyronine can enhance warfarin's anticoagulant effect. So INR should be monitored more closely when starting, stopping, or changing liothyronine dose.
Diabetes medications
Starting or increasing liothyronine can raise insulin or oral antidiabetic drug requirements. So closer blood glucose monitoring helps during dose changes.
Digoxin
Liothyronine can reduce digoxin's effect. So digoxin levels may need monitoring.
Estrogens (HRT, combined oral contraceptives)
Estrogens increase thyroxine-binding globulin, which affects both T4 and T3 levels. So dose adjustments may be needed when starting or stopping estrogens.
Antiepileptics
Carbamazepine, phenytoin, and phenobarbital increase liothyronine metabolism. So dose increases may be needed.
Rifampicin
Rifampicin (used for tuberculosis and other infections) increases liothyronine metabolism. So dose increases may be needed.
Amiodarone
Amiodarone has complex effects on thyroid function. So patients on amiodarone need specialist thyroid function monitoring.
Cholesterol medications
Cholestyramine and colestipol reduce thyroid hormone absorption. So space by at least 4 hours.
Beta-blockers
Beta-blockers like propranolol are often used to control cardiac symptoms in patients starting thyroid hormone treatment. Also, propranolol may reduce T4-to-T3 conversion at high doses, though this matters less on liothyronine (where you're taking T3 directly).
Food and drink
Food may reduce liothyronine absorption. Particularly, coffee, dairy products, high-fibre foods, and soy products may affect absorption. So consistent timing around meals matters.
Alcohol
Moderate alcohol doesn't directly interact with liothyronine.
Frequently asked questions about Liothyronine 20mcg
What is liothyronine used for?
Liothyronine (T3) is a specialist second-line thyroid hormone used for hypothyroidism in patients who don't feel fully well on levothyroxine (T4) alone, or for specific situations like severe hypothyroidism, myxoedema coma, or thyroid cancer management.
How is liothyronine different from levothyroxine?
Levothyroxine (T4) is the storage/transport form of thyroid hormone with a 7-day half-life, taken once daily. Liothyronine (T3) is the active hormone with a 1-day half-life, needing 2-3 daily doses. Also, T3 acts rapidly (hours) while T4 acts slowly (days-weeks).
Is liothyronine better than levothyroxine?
Not for most patients. Because levothyroxine works well for the vast majority of people with hypothyroidism and has a longer safety record, it's the first-line treatment. However, a small proportion of patients may benefit from adding liothyronine after specialist assessment.
Do I need to see an endocrinologist?
For starting liothyronine, yes. Because NICE doesn't recommend routine use, specialist assessment is expected before initiation. Also, ongoing monitoring benefits from at least periodic specialist review, though we can support stable repeat prescriptions between reviews.
How often do I take liothyronine?
Usually 2-3 times daily, spread through the day, due to the short half-life. So morning, midday, and evening dosing is common, or morning and evening for twice-daily regimens.
Can I take liothyronine once daily?
Some patients on very low doses (5-10mcg daily as combination therapy with T4) can take it once daily. However, higher doses usually need dividing to keep blood levels reasonably steady. So follow your endocrinologist's specific advice.
Should I take liothyronine on an empty stomach?
Evidence is less clear than for levothyroxine, but many prescribers recommend empty-stomach dosing for the morning dose at least. So follow your prescriber's specific guidance.
How quickly will I feel better?
Effects can appear within hours to days, faster than with levothyroxine. However, assessing overall benefit takes at least 3 months of stable dosing, per BTA guidance.
How long will I take liothyronine?
If the trial is successful, treatment is usually long-term. However, if there's no clear benefit at 3-6 months, specialist review to consider stopping and reverting to levothyroxine monotherapy is appropriate.
What monitoring do I need?
Free T3, free T4, and TSH blood tests (usually every 3-6 months during titration, at least annually when stable). Also, clinical symptom assessment matters, and periodic ECG or bone density scans may be recommended based on your individual risks.
Can I combine liothyronine with levothyroxine?
Yes, and this is the most common way liothyronine is used in the UK. Because combination therapy aims to replicate more normal thyroid physiology, T4 doses are usually reduced when T3 is added.
What if I miss a dose?
Take it as soon as you remember. However, if it's close to your next dose, skip the missed one. Don't double up. Because T3 has a short half-life, missed doses cause more noticeable effects than with T4, but occasional misses don't cause immediate problems.
Can I take liothyronine during pregnancy?
Levothyroxine is preferred in pregnancy. So contact your endocrinologist urgently if you become pregnant while on liothyronine.
Can I take liothyronine while breastfeeding?
Small amounts pass into breast milk. So specialist input is recommended, particularly at higher T3 doses.
What if I have heart disease?
Liothyronine has more cardiac safety concerns than levothyroxine. So starting doses in cardiac patients should be very low (2.5-5mcg), adjustments should be very slow, and specialist supervision is essential. Many endocrinologists avoid liothyronine in significant cardiac disease.
Can I use liothyronine for weight loss?
Absolutely not. Because using thyroid hormone for weight loss in people with normal thyroid function is dangerous (causing heart rhythm problems, bone loss, muscle wasting) and doesn't work sustainably, this use is inappropriate.
What are the signs I'm taking too much?
Palpitations, fast heart rate, tremor, sweating, heat intolerance, weight loss, anxiety, insomnia, or diarrhoea. So contact us or your endocrinologist promptly if you notice these.
What are the signs I'm taking too little?
Worsening tiredness, weight gain, cold intolerance, constipation, brain fog, or low mood. So report these too.
Why is liothyronine so expensive?
Liothyronine had extreme price rises in the UK between 2007 and 2016 (around 6,000% increase), reaching over £250 per pack. However, following a CMA investigation and generic competition, prices have come down to around £50 per pack. So it's still much more expensive than levothyroxine but much better than at the peak.
Do I need a prescription?
Yes. Liothyronine is a Prescription-Only Medicine (POM). So our online prescriber service can supply repeat prescriptions for patients established under specialist care, or refer you for endocrinologist assessment if that's needed first.
How should I store liothyronine?
Below 25°C in the original packaging, away from direct sunlight and moisture. Keep out of reach of children.
Disclaimer
Disclaimer: This information is for education only and isn't a substitute for personal medical advice. Liothyronine is a specialist Prescription-Only Medicine and should only be taken when prescribed after specialist endocrinologist assessment. It's not intended to diagnose, treat, cure, or prevent any condition without prescriber assessment. NICE does not recommend routine use of liothyronine for primary hypothyroidism. Regular blood test monitoring (fT3, fT4, TSH) and periodic endocrinologist review are essential. Contact your prescriber, endocrinologist, or A&E urgently for chest pain, severe palpitations, new irregular heartbeat, signs of adrenal crisis, or signs of severe allergic reaction. Liothyronine should never be used for weight loss in people without confirmed hypothyroidism.
National Institute for Health and Care Excellence (2019, updated 2023) Thyroid disease: assessment and management. NG145. Available at: https://www.nice.org.uk/guidance/ng145