



Introduction
Testosterone replacement therapy (TRT) has traditionally been given by intramuscular (IM) injection into a large muscle, such as the buttock or thigh. For some people, IM injections can be uncomfortable, cause anxiety or be difficult to self-administer. This has led to growing interest in subcutaneous (SC) injection, which delivers the medicine into the fatty tissue just beneath the skin.
Testosterone cypionate, a commonly used injectable form of testosterone, has been given subcutaneously in several clinical studies. Early results suggest that SC injections can achieve therapeutic testosterone levels, and many participants found them easier and less painful than IM injections. However, the research so far comes from small studies and clinic cohorts. Questions also remain about long-term safety, including effects on red blood cell levels. [1], [2], [6]
This article sets out what the evidence shows so far, what may make the SC route appealing, and why monitoring remains essential whichever route is used.
Key takeaways
- Testosterone cypionate has been given by SC injection in several small clinical studies, and participants reached therapeutic testosterone levels.
- A small crossover study found that overall testosterone exposure was similar with SC and IM injection, although levels varied considerably between individuals.
- Participants reported less pain and less injection-related anxiety with SC injections, and in one cohort, all 22 people who switched from IM to SC preferred SC.
- Erythrocytosis (a raised red blood cell concentration) has been reported during SC cypionate treatment, so regular blood monitoring is still essential.
- The evidence is still limited, so any change in route, dose or technique should be agreed with the prescribing clinician.
Can testosterone cypionate be injected via subcutaneous injection?
Yes—testosterone cypionate has been administered by subcutaneous (SC, under-the-skin) injection in clinical studies. Small studies and clinical cohorts suggest SC injections can achieve therapeutic testosterone levels, and one small crossover study found comparable overall testosterone exposure with SC and intramuscular (IM) injection. The evidence is promising but limited: it does not establish that every cypionate product is intended for SC use, that the route is best for every patient, or that monitoring can be skipped. [1], [2]
What “subcutaneous” means
An SC injection places medicine in the fatty tissue just beneath the skin; an IM injection places it in muscle. The two routes differ in the tissue receiving the injection, so a change in route should be treated as a clinician-guided change—not as an automatic instruction to use the same dose and technique. [1], [3]
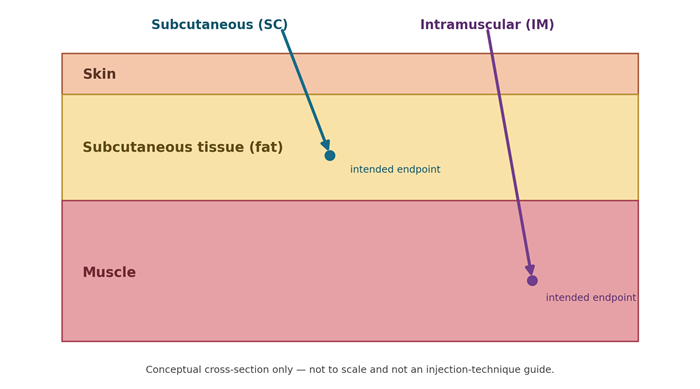
Conceptual cross-section contrasting SC and IM injection target layers; not to scale and not a technique guide.
Figure 1. Conceptual illustration of the tissue layers. This is not to scale and does not specify needle, site, dose, or technique.
Does SC cypionate work?
The direct evidence includes several small studies in which testosterone cypionate was one of the medicines given SC. In a study of 11 transgender men already receiving weekly SC cypionate, total and free testosterone levels were measured at eight points over the weekly interval. Average levels remained stable and within the study’s stated normal range; the investigators reported no adverse effects. Because participants were already established on treatment and the sample was small, this result demonstrates feasibility rather than proving equal outcomes for every patient or indication. [4]
A retrospective clinic cohort followed 63 adults receiving weekly SC testosterone cypionate or enanthate, with starting doses adjusted to reach the target testosterone range. All 63 achieved the study’s target range at doses from 50 to 150 mg; nine reported minor, transient local reactions. Among 22 people who switched from IM to SC, all preferred SC to some degree. Since the study combined two testosterone esters and had no randomised comparison group, its results support SC testosterone generally but do not isolate the effect of cypionate alone. [5]
A small prospective crossover study provides a more direct comparison of injection routes. Fourteen participants who had been stable on IM testosterone cypionate or enanthate used IM injections for three weeks and then SC injections for eight weeks. Dose-normalised testosterone exposure was comparable between routes, although the study reported substantial variability between individuals. Participants’ questionnaires favored SC for pre-injection anxiety and pain during and after injection. The small sample and short follow-up limit conclusions about long-term safety or differences between cypionate and enanthate. [2]
Taken together, a systematic review of SC testosterone studies concluded that available—though limited—evidence supports comparable pharmacokinetics and average testosterone levels at doses similar to IM treatment, and that SC self-administration can be feasible after appropriate training. The review also emphasised that stronger direct safety comparisons are needed. [1]
What may be appealing about the SC route
For some people, SC injections may be easier to self-administer and less uncomfortable than IM injections. In the crossover study, participants reported lower injection-related anxiety and pain with SC administration; in the 63-person retrospective cohort, all 22 people who moved from IM to SC expressed at least a mild preference for SC. These are patient-reported findings from particular samples, not a guarantee that SC injections will be less painful for everyone. [2], [5]
The evidence does not support the assumption that SC is universally safer or more effective than IM. In a retrospective review of 94 men receiving SC testosterone cypionate, 32% developed new-onset erythrocytosis (an elevated red-cell concentration). The authors compared this rate with published IM rates, rather than with a concurrent randomised IM group, and called for further study. This finding is an important reminder that changing the injection route does not remove the need for appropriate clinical follow-up. [6]
Another retrospective series of 41 men receiving SC cypionate reported an increase in hematocrit during follow-up, although the increase was not statistically significant and no participant developed erythrocytosis in that cohort. The difference between this finding and the 94-person cohort illustrates why small, non-randomied studies should not be used to promise an individual safety outcome. [6], [7]
What should be monitored?
SC administration changes the injection route; it does not make testosterone therapy self-monitoring-free. Published studies assessed serum testosterone and blood measures such as hemoglobin or hematocrit. The 94-person SC-cypionate study specifically evaluated hematocrit, while other SC studies also followed testosterone concentrations and, depending on the population, estradiol or other clinical measures. These study measurements illustrate the issues clinicians have tracked; the abstracts reviewed here do not establish one monitoring schedule for every patient. [2], [5], [6]
Dose, timing of blood tests, injection supplies, and technique should therefore be confirmed with the prescribing clinician or pharmacist for the individual product and treatment plan. A person should not infer a dose conversion or change route based only on studies involving a different ester, device, population, or dosing schedule. The available research includes both cypionate and enanthate, and some comparisons combine them rather than reporting separate route effects. [1], [2], [5]
Conclusion
The evidence supports a measured answer: SC testosterone cypionate can work, and it may be a practical alternative to IM injection for some patients when prescribed and taught by a clinician. Small cypionate cohorts report therapeutic levels, and limited route-comparison data suggest similar overall testosterone exposure; however, long-term head-to-head safety evidence remains incomplete, and erythrocytosis has been reported during SC cypionate treatment. The right route and follow-up plan depend on the product and the patient, and both need to be factored in by the treating clinician rather than changing the route independently. [1], [2], [4], [6]
References
[3] S. S. Montoto and M. E. Ruiz, “Intramuscular drug delivery,” The ADME Encyclopedia, 2022
[4] J. McFarland, W. Craig, N. J. Clarke, and D. I. Spratt, “Serum testosterone concentrations remain stable between injections in patients receiving subcutaneous testosterone,” Journal of the Endocrine Society



